We're changing the way Sapphire looks
Same platform, new visual identity. Learn more: Sapphire is becoming NHMRC Grant Management System.
We're changing the way Sapphire looks
Same platform, new visual identity. Learn more: Sapphire is becoming NHMRC Grant Management System.
For the review of the evidence for dietary guidance for older Australians.
Published in June 2024.
In late-2023 the Department of Health and Aged Care requested that the NHMRC provide advice for older Australians to support health and wellbeing as an additional component of the revision of the Australian Dietary Guidelines. This guidance will cover the general population aged 65 years and older (or 50+ years for Aboriginal and Torres Strait Islander peoples). The guidance will not apply to people with medical conditions that require specialised diets for managing disease or frailty. However, it is aimed at supporting prevention of malnutrition, frailty, falls and chronic conditions.
This document describes the process the Dietary Guidelines Expert Committee (the Expert Committee) used to shortlist topics and research questions for older Australians to target the scope of the evidence review within the available resources.
The Prioritisation Process Report for the review of the evidence underpinning the broader Australian Dietary Guidelines can be found on the NHMRC website. This information also helped inform the prioritisation work undertaken for the Guidelines for Older Australians. The Prioritisation Process Report for Older Australians includes:
Section 1 – Scoping activities – describes activities which contributed to Expert Committee consideration of a broad list of topic areas relevant to nutrition and food-based advice for older Australians.
Section 2 – Topic prioritisation – this is similar to the Expert Committee process to reach a refined list of topic areas for the broader guideline revision (more information can be found in can be found in the Prioritisation Process Report).
Section 3 – Next steps for developing dietary guidance for older Australians
During 2020 and 2021, NHMRC carried out scoping activities for the revision of the broader Australian Dietary Guidelines. Scoping activities were intentionally broad, involving web searches, literature database searches and media platform searches. Direct input was sought from stakeholders through surveys and targeted consultation on various aspects of the 2013 Guidelines and companion resources, such as the Australian Guide to Healthy Eating and the Aboriginal and Torres Strait Islander Guide to Healthy Eating.
Specific scoping activities undertaken for the older Australians review included:
The Expert Committee had previously identified priority research topics and healthy ageing specific outcomes during the prioritisation process for the broader Australian Dietary Guidelines. To do so, Expert Committee members participated in a series of surveys and discussions to agree on a shortlist of topic areas using the principles outlined below.
Prioritisation for older Australians followed the same principles for prioritising topics as the previous work that was done for the broader Australian Dietary Guidelines. This process occurred in April 2024.
The following principles were applied by the Expert Committee when prioritising the topics for the broader Australian Dietary Guidelines and when considering the shortlisted topics during topic prioritisation for older Australians:
The principles were modelled on the prioritisation pathways used for development of the Dietary Guidelines for Americans 2021–25, the Nordic Nutrition Recommendations 2022, and Canada’s Dietary Guidelines. The principles also took into consideration prioritisation criteria commonly used in the development of health practice guidelines.1
More information on the prioritisation principles can be found in Prioritisation Process Report for the review of the broader Australian Dietary Guidelines.
The list of potential topic areas was developed using results from the scoping activities (see Section 1). The following broad topics were shortlisted to inform development of the research questions and scope of the evidence review update:2
The Expert Committee considered the potential topics for older Australians using the prioritisation principles. Many topics were considered to be covered by the research questions already identified during prioritisation for the broader Australian Dietary Guidelines revision (Tables 1–5). Others were identified as being able to be addressed by alternative avenues (for example sodium, alcohol; Table 6). Some were out of scope as they were not related to whole foods or dietary patterns or were considered to be implementation issues (Tables 7–8).
The Expert Committee advised the previously identified Dietary Guidelines review questions were relevant to, and are a priority for, older Australians. The Expert Committee advised that no new topics were required.
Expert Committee members advised that contextual factors that affect older Australians, and are barriers to consuming a diet aligned with the guidelines, may be different from those that affect the general population. Contextual factors considered of particular relevance include:
In addition, provision of food by residential aged care facilities may be a barrier to consuming a diet aligned with the guidelines.
As part of the broader Dietary Guidelines revision, the Expert Committee identified the following outcomes as being of interest:
Following the scoping for older Australians the Expert Committee advised that outcomes specifically relevant to older Australians should be added:
| Question/subtopic | Populations | Interventions/ exposures, comparisons | Outcomes | Notes |
|---|---|---|---|---|
Dietary patterns and health outcomes Dietary patterns must be relevant at a population level. Excludes interventions/ exposures that are for treatment of disease e.g., diabetes, CVD | Older Australians Defined as adults 65+ years or Aboriginal and Torres Strait Islander people aged 50+ | Dietary patterns vs other dietary patterns OR High similarity to a specific dietary pattern vs low similarity to that dietary pattern | Relevant health outcomes
Chronic condition risk factors
Healthy Ageing
| Considered to cover the following topics identified in scoping activities:
|
Intake of animal vs plant sources of protein and health outcomes Excludes interventions/ exposures that are for treatment of disease e.g., diabetes, CVD | Older Australians Defined as adults 65+ years or Aboriginal and Torres Strait Islander people aged 50+ | Protein intake from plant-based sources vs protein intake from animal sources high vs low intake of plant foods | Relevant health outcomes
Chronic condition risk factors
Healthy Ageing
| Considered to cover the following topics identified in scoping activities:
|
| Question/subtopic | Populations | Interventions/ exposures, comparisons | Outcomes | Notes |
|---|---|---|---|---|
Ultra-processed food intake and health outcomes Exclude interventions/ exposures that are for treatment of disease e.g., diabetes, CVD | Older Australians Defined as adults 65+ years or Aboriginal and Torres Strait Islander people aged 50+ | High intake of ultra-processed foods vs no/low intake of ultra-processed foods | Relevant health outcomes
Chronic condition risk factors
Healthy Ageing
| Considered to cover the following topics identified in scoping activities:
|
| Question/subtopic | Populations | Interventions/ exposures, comparisons | Outcomes | Notes |
|---|---|---|---|---|
Frequency of eating and health outcomes Exclude interventions/ exposures that are for treatment of disease e.g., diabetes, CVD | Older Australians Defined as adults 65+ years or Aboriginal and Torres Strait Islander people aged 50+ | Frequency of eating vs Different meal pattern frequency OR varying levels of frequency of eating OR different meals patterns | Relevant health outcomes
Chronic condition risk factors
Healthy Ageing
| Considered to supplement the dietary patterns question above and cover the following topics identified in scoping activities:
|
| Question/subtopic | Populations | Interventions/ exposures, comparisons | Outcomes | Notes |
|---|---|---|---|---|
Meats, poultry, fish, eggs, nuts and seeds, legumes/beans (including pulses and tofu) Exclude interventions/ exposures that are for treatment of disease e.g., diabetes, CVD | Older Australians Defined as adults 65+ years or Aboriginal and Torres Strait Islander people aged 50+ | Red meat intake vs white meat OR High intake of legumes/ pulses vs No/ low intake of legumes/ pulses | Relevant health outcomes
Chronic condition risk factors
Healthy Ageing
| Considered to supplement the dietary patterns question above and cover the following topics identified in scoping activities:
|
| Question/subtopic | Populations | Interventions/ exposures, comparisons | Outcomes |
|---|---|---|---|
| Influence of eating environment/ context and consumption aligned with guidelines | Older Adults Defined as adults 65+ years or Aboriginal and Torres Strait Islander people aged 50+ Subpopulations of interest: Priority populations identified in the National Preventive Health Strategy 2021 -2030:
| Factors relating to eating environment/ context, including:
Exclude interventions/ exposures that are for treatment of disease e.g., diabetes, CVD | Consumption aligned with guidelines (at point in time; life course) |
| Barriers and enablers to consumption aligned with guidelines | Older Adults Defined as adults 65+ years or Aboriginal and Torres Strait Islander people aged 50+ Subpopulations of interest: Priority populations identified in the National Preventive Health Strategy 2021 -2030:
| Other barriers and enablers to consumption of foods aligned with guidelines e.g., food literacy/skills
Exclude interventions/ exposures that are for treatment of disease e.g., diabetes, CVD | Consumption aligned with guidelines (at point in time; life course) |
| Barriers and enablers to consumption aligned with guidelines | Older Adults Defined as adults 65+ years or Aboriginal and Torres Strait Islander people aged 50+ Subpopulations of interest: Priority populations identified in the National Preventive Health Strategy 2021 -2030:
| Food security Exclude interventions/ exposures that are for treatment of disease e.g., diabetes, CVD | Consumption aligned with guidelines (at point in time; life course) |
| Interventions /strategies to improve dietary patterns and eating behaviours aligned with the guidelines across the life course | Older Adults Defined as adults 65+ years or Aboriginal and Torres Strait Islander people aged 50+ Subpopulations of interest: Priority populations identified in the National Preventive Health Strategy 2021 -2030:
| Interventions Exclude interventions/ exposures that are for treatment of disease e.g., diabetes, CVD | Consumption aligned with guidelines (at point in time; life course) |
| Question/ Subtopic | Rationale for priority |
|---|---|
| Sodium / salt intake and health outcomes | Sodium/salt intake and health outcomes to be addressed based on existing NHMRC evidence reviews / recommendations (NRVs 2017 and current update) |
| Alcohol intake and health outcomes | Alcohol intake and health outcomes to be addressed based on existing NHMRC evidence reviews / recommendations (NHMRC Alcohol Guidelines 2020) |
| Food safety outcomes | Food safety aspects to be addressed based on existing National food safety advice, e.g., Food Safety Information Council |
| Physical activity levels | Physical activity aspects to be addressed based on National Physical Activity Guidelines |
| Adequate fluid intake | Considered during evidence to decision process |
| Question/ Subtopic | Rationale for priority |
|---|---|
| Effects of medicines on nutrition | Not related to whole foods, food groups or dietary patterns |
| Micronutrients (vitamin B, vitamin D, zinc, etc) | Not related to whole foods, food groups or dietary patterns |
| Supplements | Not related to whole foods, food groups or dietary patterns |
| Question/ Subtopic | Rationale for priority |
|---|---|
| Guidelines as stand alone | Implementation |
| Specific resource for older Australians | Implementation |
To make efficient use of the limited review resources, recent, high quality published systematic reviews addressing the priority research questions will be used where available. A limited number of new evidence reviews will be commissioned, to target key gaps identified in the evidence base. To facilitate this approach, the next phase of the review for older Australians will comprise:
Potentially relevant systematic reviews will be identified and sourced via:
This process aims to identify suitable (current, comprehensive and methodologically robust) systematic reviews for each priority research question.4 It does not aim, or purport, to comprehensively search for and identify every relevant systematic review for the broad priority research questions identified.
Please see the Prioritisation Process Report for the broader Australian Dietary Guidelines for details on how lower priority research questions will be addressed.
Systematic reviews identified through the literature searches and public call will be collated and screened against eligibility criteria (including minimum methodological criteria). The risk of bias of potentially eligible reviews will then be assessed.
Eligible systematic reviews will be mapped against the research questions to allow the Expert Committee to consider options for addressing each priority research question and identify gaps in the underlying evidence base, that may be targeted by a newly commissioned evidence review.
Very high or high priority research questions that are unable to be addressed within the available resources will be noted as evidence gaps to inform future reviews.5
Figure 1 provides an overview of the next steps for how information from the literature search and public call will be considered.
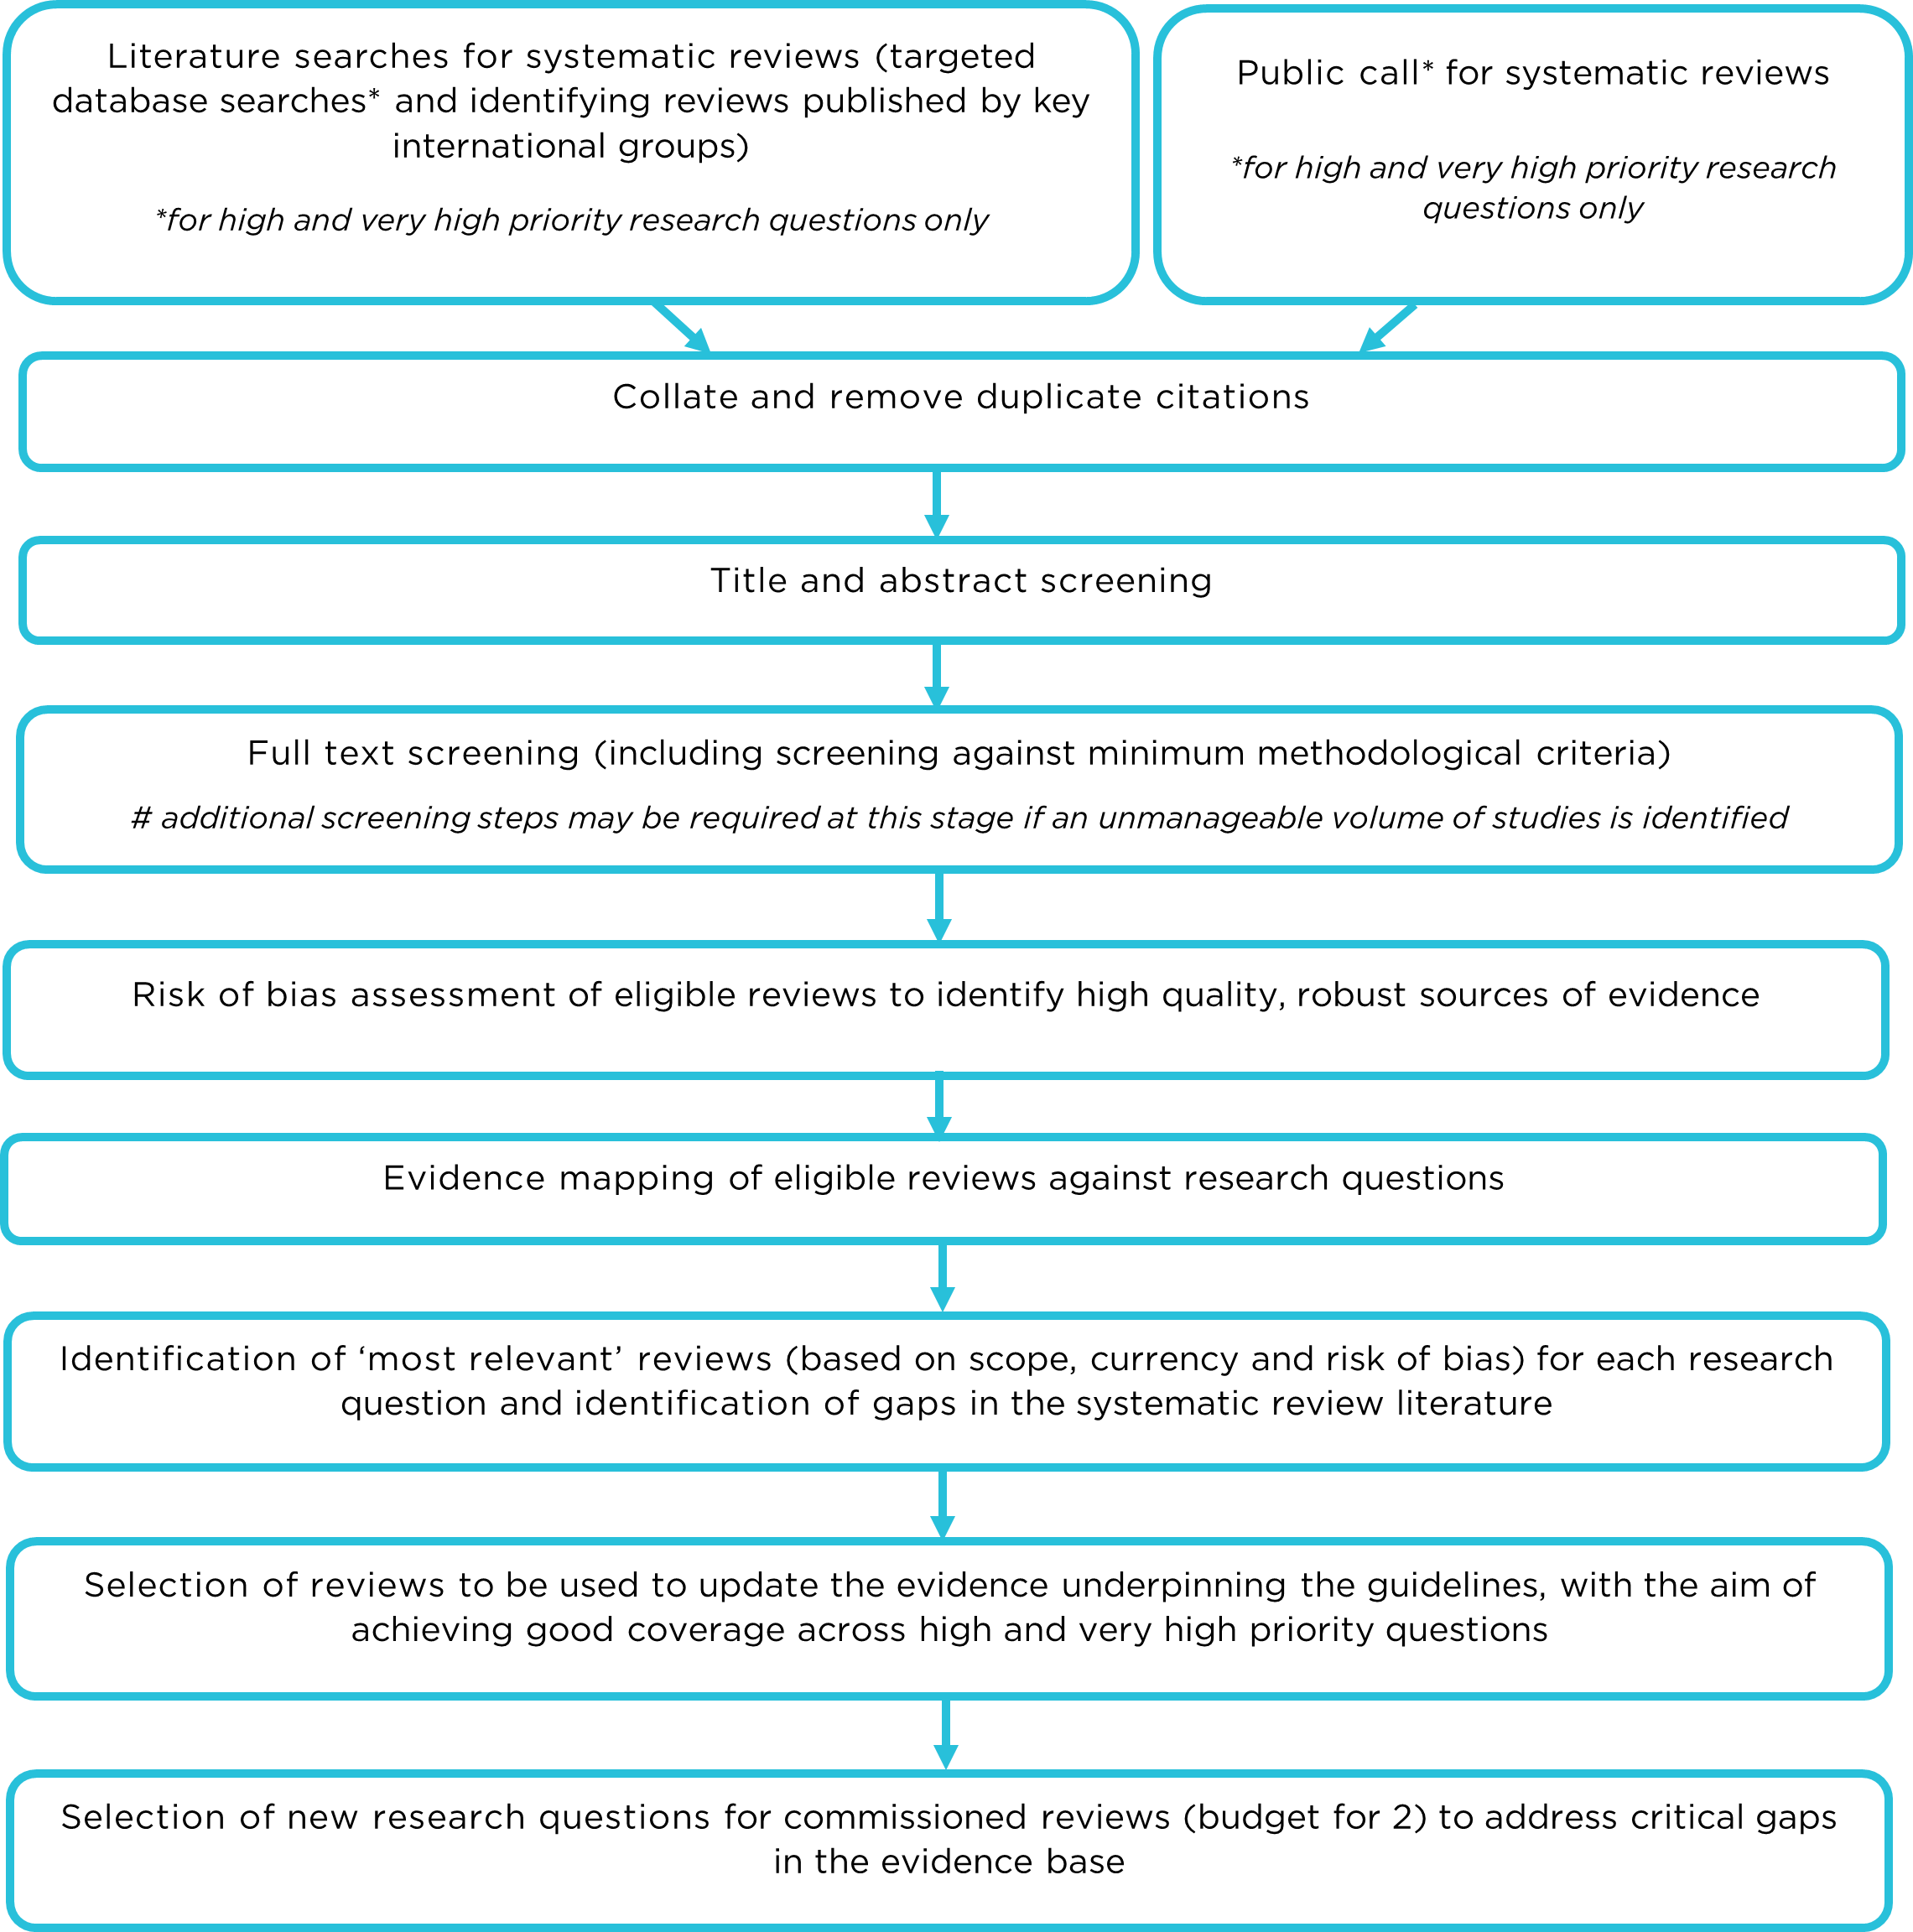
Description of Figure 1 - Overview of scoping and evidence mapping process:
*for high and very high priority research questions only
1 El-Harakeh, A., Morsi, R.Z., Fadlallah, R., Bou-Karroum, L., Lotfi, T., Akl, E.A., 2019. ‘Prioritization approaches in the development of health practice guidelines: a systematic review’, BMC Health Services Research, 19: 692.
2 The list was ranked using prioritisation principles and considering whether the evidence for a topic was likely to have changed significantly since the 2013 guidelines.
3 ‘Key international groups’ with robust methodological processes similar to NHMRC standards (https://www.nhmrc.gov.au/guidelinesforguidelines/standards) identified based on the process adopted by the 2022 Nordic Nutrition Recommendations Group
4 The Expert Committee noted a five-year cut off is common when searching for systematic reviews, the reviews themselves may include primary studies published prior to this. In addition, the revised Guidelines are anticipated for release in 2026 and any systematic review completed prior to 2018 would not consider subsequent recent studies.
5 Funding for the review allows the commissioning of up to 5 de novo reviews, depending on cost and scope.